Vermont Department of Taxes Forms & Instructions
Vermont Quarterly Withholding Reconciliation (WHT-436, 2025)
# Vermont Department of Taxes 133 State Street Montpelier, VT 05633-1401
Phone: (802) 828-2551
# HEALTH CARE CONTRIBUTIONS WORKSHEET
VT Form
HC-1
Do not return this form to the
Vermont Department of Taxes.
You must retain this form for your records for three years.
Employer FEIN Quarter / Year
Uncovered Employee Count:
Did you have 5 or more full-time equivalent (FTE) employees who were all age 18 and older in the previous quarter?. . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . Yes No
- If you answered NO, check this box to certify no Health Care Fund Contributions will be due for this quarter. Also, check the box on Form WHT-436, Line 10.
- If you answered YES, complete Section 1 or 2 below (not both) depending on the health care coverage offered by your company.
Note: For Sections 1 and 2, do not report more than 520 hours for any individual employee, no matter how many actual hours the employee worked during the calendar quarter.
Section 1: Complete this if you do not offer to pay any part of the cost of health care coverage for any of your employees.
Enter the total number of hours worked by all employees you employed during the reporting quarter and continue to "Section 3: Calculations Section," Line A. . . . . . . . . . . . . . __ Section 1: Total hours of uncovered employees
Section 2: Complete this if you do offer to pay part or all of the cost of health care coverage for any of your employees.
Enter the total number of hours worked by all employees in each of the following two categories:
- Employees who are offered and eligible for coverage but choose not to accept the coverage and have no other health care coverage or have Medicaid or who are full-time employees and have health care coverage as individuals through the Vermont Health Benefit Exchange. . . . __ Section 2, Line 1: Hours worked by employees offered coverage but did not accept.
- Employees who are not eligible for the health care coverage offered to any other employees.
You may exclude hours worked by a seasonal or part-time employee as long as you offer health care coverage to all regular, full-time employees, and the employee is covered by a plan other than Medicaid. . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . __ Section 2, Line 2: Hours worked by employees not offered coverage.
Section 3: Calculations Section
A. Enter the total hours worked by all employees entered in Section 1 or the total of Lines 1 and 2 in Section 2. NOTE: If the total is a partial hour, round down to the nearest hour..A. _ __
B. Divide the number of hours on Line A by 520. This is your unadjusted FTE count. NOTE: Round down to the nearest whole number.. . . . . . . . . . . . . . . . . . . . . . . . . B. _ __
C. Number of exempted FTEs. . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . C. _ __
D. Subtract Line C from Line B. This is your adjusted and reportable FTE count. Enter this amount on Form WHT-436, Line 11. If equal to or less than zero, report -0-. . . . . . . . D. _ __
E. Multiply Line D by the appropriate amount shown in the table below. This is your quarterly Health Care Contribution. Enter this amount on Form WHT-436, Line 12, even if -0-. . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . E. _ __ 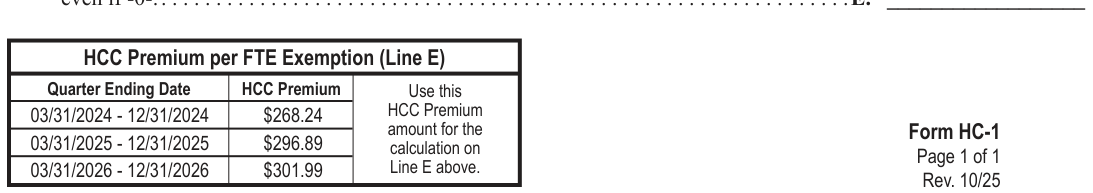
Text version of this table
HCC Premium per FTE Exemption (Line E) Quarter Ending Date HCC Premium Use this HCC Premium amount for the calculation on Line E above. 03/31/2024 - 12/31/2024 $268.24 03/31/2025 - 12/31/2025 $296.89 03/31/2026 - 12/31/2026 $301.99
Vermont Department of Taxes 133 State Street Montpelier, VT 05633-1401
Phone: (802) 828-2551
QUARTERLY WITHHOLDING
VT Form
RECONCILIATION and
# REQUIRED CONTRIBUTIONS
Text version of this table
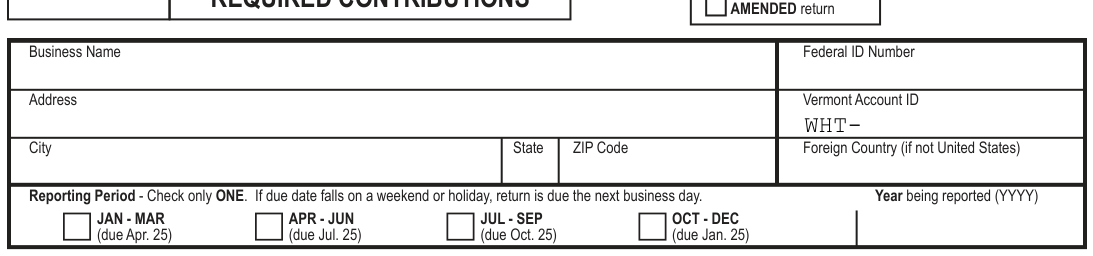
| Business Name | Federal ID Number | ||
| Address | Vermont Account ID WHT- | ||
| City | State | ZIP Code | Foreign Country (if not United States) |
| Reporting Period - Check only ONE. If due date falls on a weekend or holiday, return is due the next business day. Year being reported (YYYY) cJAN - MAR cAPR - JUN cJUL - SEP cOCT - DEC (due Apr. 25) (due Jul. 25) (due Oct. 25) (due Jan. 25) |
# Vermont Account ID
JAN - MAR APR - JUN JUL - SEP c c c
(due Apr. 25) (due Jul. 25) (due Oct. 25)
A. Number of employees as of the last day of this quarter.
PART I WAGE WITHHOLDING
Year being reported (YYYY)
# OCT - DEC
c
(due Jan. 25)
Full-time _ Part-time_
- Total Vermont wages paid this quarter . . . . . . . . . . . 1. _ _._
- Total Vermont tax withheld from wages this quarter . . . . . . . . . . . . . . . . . . . . . . . . .. . . . . . 2. _._
# PART II NONWAGE WITHHOLDING
- Total nonwage payments subject to withholding this quarter. . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . 3. _ _._
- Total Vermont tax withheld from nonwage payments this quarter. . . . . . . . . . . . . . .. . . . . . 4. _._
- Total Vermont tax withheld this quarter (Add Lines 2 and 4). . . . . . . . . . . . . . . .. . . . . . 5. _._
# PART III CHILD CARE CONTRIBUTIONS
- c Check here to certify that no Child Care Contribution is due based on the rules governing this reporting.
- Total wages subject to Child Care Contribution (see instructions). . . . . . . . . . . . . . . . . . . . . . . . . . . . 7. _ _._
- Child Care Contributions due. (Multiply Line 7 by 0. 44% (0. 0044). . . . . . . . . . . . .. . . . . . 8. _._
- Amount of Child Care Contributions contributed by employees. . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . 9._._
# PART IV HEALTH CARE CONTRIBUTIONS
- c Check here to certify that no Health Care Contribution is due based on the rules governing this reporting.
- Adjusted Uncovered FTE (from Form HC-1, Health Care Contributions Worksheet, Line D) . . . 11. _ __
- Total Health Care Contributions Due (from Form HC-1, Line E) . . . . . . . . . . . . . . .. . . . . 12._._
# PART V BALANCE
- Total due (Add Lines 5, 8, and 12). . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . . .. . . . . 13. _._
- Vermont withholding tax and contributions already paid this quarter . . . . . . . . . . . .. . . . . 14. _._
- Refund (If Line 14 is greater than Line 13, subtract Line 13 from Line 14. ). . . . . . .. . . . . 15. _._
- TOTAL Withholding Tax, Child Care Contributions, and Health Care Contributions Due (If Line 13 is greater than Line 14, subtract Line 14 from Line 13. ) . . . . . . . . . . . . .. . . . . 16. _._
# PART VI SIGNATURE
I hereby certify that I have examined this return and to the best of my knowledge and belief it is true, correct, and complete.
Signature of Officer or Authorized Agent Date
Title Telephone Number
Preparer's Signature Date
Firm's name (or yours, if self-employed) and address
Preparer's Telephone Number
Check here if authorizing the Vermont
Department of Taxes to discuss this return and attachments with your preparer.
Preparer's PTIN or EIN
Rev. 10/25
Save and go to Important Printing Instructions
Clear period info only Clear ALL fields Save and Print
Source: view the official PDF
Nearby sections (13 sections)
- bi-477 · Vermont Income Adjustment Calculation: Pass-Through Vermont…
- co-411-corporate-instructions · Vermont Corporate Income Tax Return…
- co-414-corporate-estimated · Vermont Corporate Estimated Tax Payment…
- est-191-estate-instructions · Vermont Estate Tax Return Instructions…
- fit-161-fiduciary-instructions · Vermont Fiduciary Income Tax Return…
- hs-122-homestead-instructions · Vermont Homestead Declaration and…
- in-111-income-booklet · Vermont Income Tax Return Booklet (IN-111) —…
- in-114-individual-estimated · Vermont Individual Estimated Income Tax…
- in-152-underpayment · Vermont Underpayment of Estimated Tax by…
- k-1vt · Schedule K-1VT (2025) — Vermont Shareholder, Partner, or Member…
- sut-451-sales-use-return · Vermont Sales and Use Tax Return (SUT-451,…
- w-4vt-employee-withholding · Vermont Employee Withholding Allowance…
- wht-436-quarterly-withholding · Vermont Quarterly Withholding…